Healthcare AI Agents: Patient Access, Payer Calls and Clinical Boundaries
Buy the workflow, not the category. Compare healthcare AI agents for scheduling, payer calls, intake, and referral work across EHR integration depth, HIPAA diligence, identity controls, and failure-oriented pilot tests.
Buy a measurable workflow, not a “healthcare AI agent.” Appointment scheduling, referral intake, and payer-status calls use different systems, carry different failure modes, and need different vendors. This guide maps products to those jobs. It does not rank unlike products on a single ladder.
For a first deployment, prefer a bounded administrative task with an observable outcome: a booked slot, a routed referral, or a completed payer record. Diagnosis, prescribing, symptom interpretation, and urgency recommendations are outside this guide. They require separate clinical, regulatory, safety, and validation review.
The product analysis below is based on public vendor documentation reviewed in October 2026. It identifies documented capabilities and unanswered diligence questions; it is not a hands-on accuracy benchmark. Security claims, certifications, integrations, pricing, and availability must be confirmed for the contracted service and region.
This is a U.S.-focused software buyer’s guide, not medical or legal advice and not a determination of HIPAA or FDA status.
The short answer
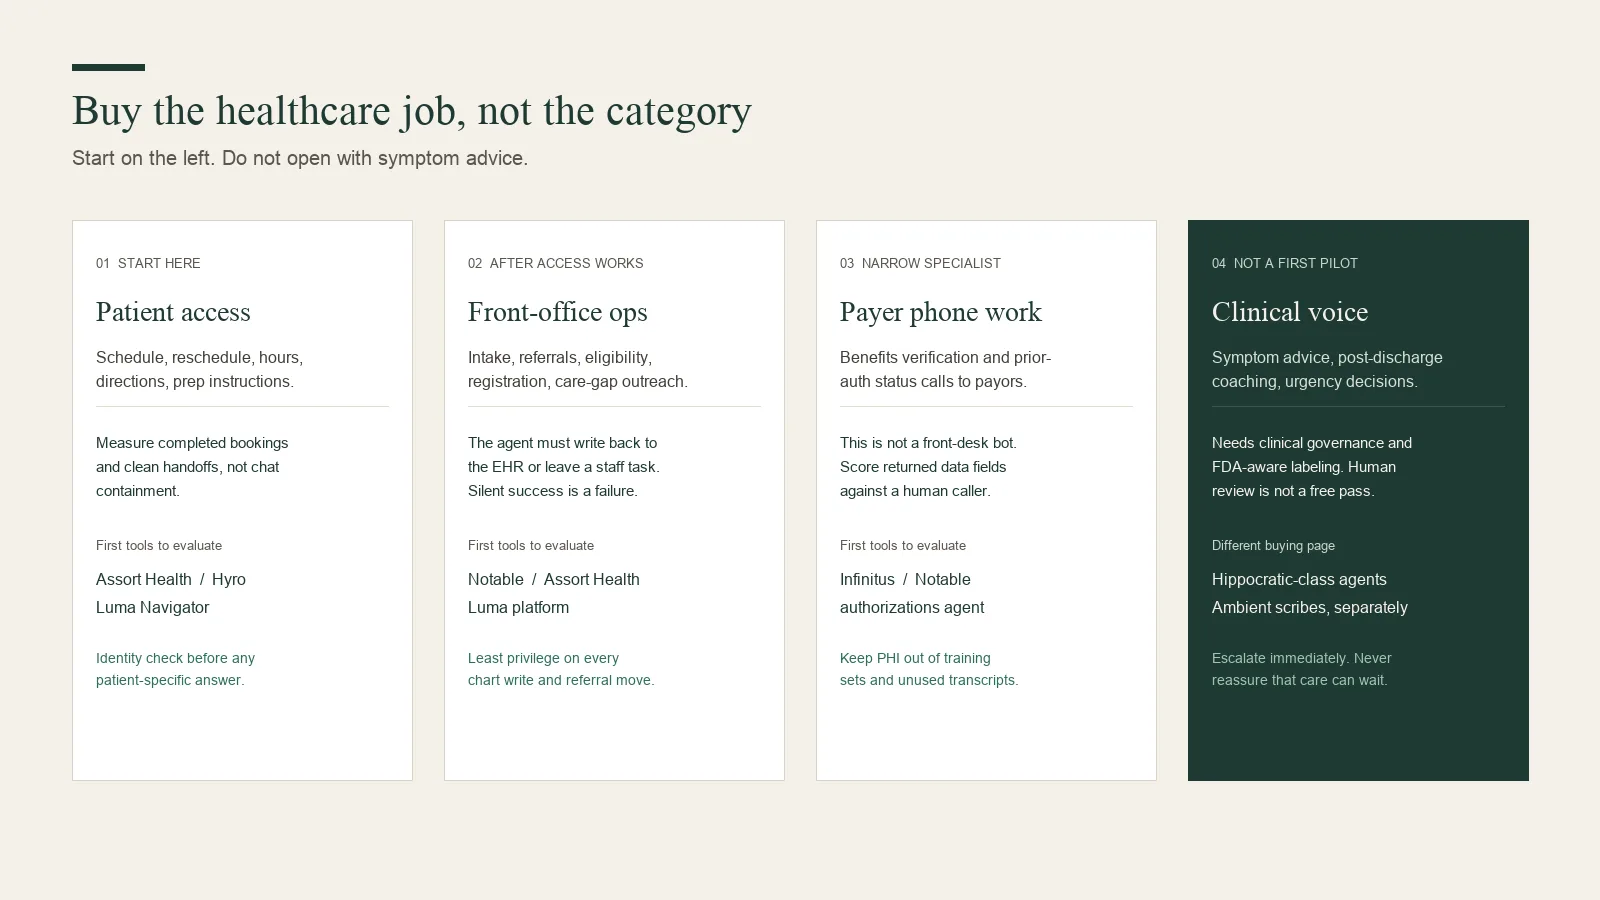
Specialty scheduling and EHR tasks: evaluate Assort Health.
Repetitive access questions across voice and web: evaluate Hyro.
Scheduling, outreach, forms, and messaging on one access platform: evaluate Luma Health Navigator.
Referral, intake, eligibility, and authorization queues: evaluate Notable.
Benefits and prior-authorization status calls to payers or PBMs: evaluate Infinitus.
These are five separate shortlists compressed into one map. Compare vendors only when they can complete the same workflow against the same test cases.
General chatbot builders are not included as healthcare recommendations. A general platform may be tested with synthetic data, but it should not receive PHI until contractual and technical evidence covers the exact service.
Test field completeness and payer refusal handling
“Sales-led” is not a price comparison. Ask each relevant vendor to quote the same volume, channels, integration scope, implementation work, support level, and contract term.
What counts as a healthcare AI agent?
For this guide, an agent receives a request, retrieves approved information, takes a permitted action, and records the result. A booked appointment, an EHR task, a routed referral, or a structured payer response counts as an action. A plausible answer with no completed work does not. That definition aligns with how AI agents are commonly understood: a system that acts on context rather than merely generating text. See the AI agent glossary for the broader definition.
The distinction matters because “contained conversation” can hide rework. Measure whether the intended record changed correctly, whether staff had to repair it, and whether the patient reached the right next step.
If the job is encounter documentation, compare AI medical scribes. If it is a non-healthcare business line with no PHI, compare AI receptionist software. Do not make one product pretend to be a scheduler, scribe, clinical triage system, and revenue-cycle platform.
Choose the first workflow
Current bottleneck
First workflow
Observable outcome
Keep outside scope
Missed calls and long scheduling queues
Schedule and reschedule
Correct slot written to the source system
Symptom or medication advice
Repetitive contact-center questions
Hours, locations, preparation, physician search
Correct answer or contextual transfer
Open-ended clinical conversation
Incomplete access work
Waitlist, recall, intake, referral follow-up
Task completed or exception owned
New clinical claims in outreach
Payer phone work
Benefits verification or authorization status
Required fields returned with provenance
Patient-facing care coaching
Public website questions
Approved public information
Answer sourced or human handoff
Patient-specific records or free-text intake
A task is not low risk merely because it is administrative. Wrong-patient disclosure, an incorrect booking, an inaccessible interface, or a missed urgent statement can still cause harm.
Buy the healthcare job, not the category. Start on the left.
The five products, evaluated by workflow
Assort Health
Evaluate for: specialty scheduling, inbound patient access, and EHR task creation.
Assort’s Concierge documentation says its voice and chat agents apply specialty scheduling logic, capture insurance and demographic details, book from live availability, and sync appointments and tasks to the EHR. Its health-system page lists Epic, Oracle Health, athenahealth, NextGen, eClinicalWorks, and other systems, and states HIPAA and SOC 2 Type II status. These are vendor claims, not proof that every object or workflow is supported in your environment.
Evidence to request: current security reports, the BAA and service schedule, a supported-interface matrix, implementation responsibilities, and references using the same EHR and specialty.
Main uncertainty: “EHR integration” can mean a link, a task, an appointment write, or a bidirectional workflow. Record the exact objects Assort can read and write, expected latency, duplicate prevention, and who repairs failed transactions.
Test: reschedule a patient with provider, payer, time, interpreter, and location constraints. Add a refill request that must become a staff task without medication advice. Repeat with two patients who share a name.
Walk away if: the demonstration uses a mock calendar, the vendor cannot show the resulting EHR record, or exceptions return to an unowned queue.
Hyro
Evaluate for: provider search, repetitive access questions, and contextual routing across the required voice and digital channels.
Hyro’s provider-search page describes helping patients find providers. Its Care OnCue platform covers a wider set of access and routing workflows. Verify the exact scheduling actions, channels, and transfer payload supported in your environment. The BAA, subprocessors, covered services, and retention terms still need contract review; a platform-level assurance does not establish the controls for your workflow.
Evidence to request: source-level answer tracing, content approval and expiry controls, redaction behavior, transfer payloads, channel-specific retention, and current security documentation.
Main uncertainty: a correct answer is not the same as a resolved request. Measure repeat contacts, wrong-department transfers, abandoned handoffs, and staff rework.
Test: run the ten most common contact reasons, one retired policy, one ambiguous physician name, one urgent statement, and one failed transfer after hours.
Walk away if: staff cannot identify the source and version behind an answer or the receiving agent gets no transcript and intent.
Luma Health Navigator
Evaluate for: organizations already buying scheduling, outreach, reminders, forms, and messaging as one patient-access program.
Luma’s product documentation describes Navigator as an inbound conversational agent. Its Spark announcement describes language switching, SMS continuation, staff handoff, and bidirectional connections with several EHRs. Luma’s security page publishes HITRUST CSF r2, SOC 2 Type II, ISO 27001:2022, TX-RAMP Level 2, zero-retention AI, and no-training claims. Confirm the reports, scope, exceptions, and downstream telephony or analytics retention in the contract.
Evidence to request: the specific Navigator skills available for your EHR, interface fees, transcript and recording data flows, language coverage by workflow, and recovery behavior when SMS or EHR services fail.
Main uncertainty: platform breadth can reduce handoffs between products, but it can also make scope and responsibility harder to see. Map every subprocessor and system write.
Test: complete an after-hours reschedule, switch channels, lose the connection, and recover without a duplicate appointment. Repeat in each supported language using approved translated content.
Walk away if: a certification list substitutes for workflow evidence or “zero retention” excludes connected systems that still keep the interaction.
Notable
Evaluate for: registration, referral, eligibility, and prior-authorization queues.
Notable’s access page describes Front Desk, Referrals, and Authorizations agents. Its authorizations page says agents gather data, submit through payer channels, update the EHR, and can trigger post-approval scheduling. The Notable Trust Center lists HITRUST, SOC 2 Type 2, ISO/IEC 27001:2022, and PCI DSS. Request current reports and verify which services are in scope.
Evidence to request: an object-level workflow map, approval rules, denial and appeal handling, staff exception queues, reconciliation reports, and customer references for the same payer mix.
Main uncertainty: “end to end” has boundaries. Document which authorization types, payers, and service lines are automated, which require staff, and what happens when eligibility data is wrong.
Test: one complete referral, one missing a document, one duplicate, one payer denial, and one EHR write failure. Require a visible owner for every exception.
Walk away if: the workflow can report completion without a matching source-system state or staff cannot reverse an incorrect write.
Infinitus
Evaluate for: benefits verification and prior-authorization status calls to payers and PBMs.
Infinitus’s current platform documentation describes benefit verification and prior-authorization follow-up within a broader patient-coordination platform. Its safety page describes topic restrictions, bias testing, and other guardrails. Request the actual BAA, security reports, redaction configuration, and deletion terms for the contracted service instead of inferring them from safety positioning.
Evidence to request: payer and therapy coverage, required-field schemas, call recordings or trace evidence, human-verification rules, deletion terms, and handling when a payer refuses an automated caller.
Main uncertainty: this evaluation covers payer-side phone work. The broader platform also describes patient and provider coordination; do not assume those workflows have the same implementation or validation requirements. For payer calls, evaluate complete and correctly attributed fields rather than conversational fluency.
Test: blind-compare a sample of recent completed calls with the agent output. Score missing fields, network-status errors, provenance, turnaround, and escalation.
Walk away if: results cannot be traced to the call, unsupported payers are not identified before submission, or low-confidence fields look final.
What is not in this comparison?
Hippocratic AI markets patient-facing clinical voice agents for care-management work. That is a different purchase from administrative access. Its published testing and outcome figures are vendor evidence; patient-facing clinical use needs its own clinical governance and validation.
Oracle Health Clinical AI Agent includes documentation, coding, and patient-access concepts inside Oracle workflows. For each access or revenue-cycle capability, confirm general availability in your deployed version rather than treating a platform roadmap as an installed feature.
DAX, Abridge, Suki, Nabla, Ambience, and similar products belong in the medical-scribe comparison. Symptom checkers and triage systems need a separate evaluation built around clinical evidence, labeling, intended use, and post-market monitoring.
General chatbot builders are also outside the shortlist. A warning that says “do not enter health information” does not prevent a patient from entering it.
The diligence framework
Privacy, security, and contracting
A vendor’s “HIPAA compliant” statement is not an approval. HHS business-associate guidance explicitly includes an AI chatbot on a patient portal when it handles PHI for services such as symptom assessment, reminders, or scheduling.
Before PHI enters the service:
Execute a BAA covering the exact products and subprocessors, including speech-to-text, text-to-speech, telephony, model hosts, analytics, and backups.
Map where PHI is created, transmitted, stored, logged, backed up, exported, and deleted.
Set retention separately for recordings, transcripts, summaries, prompts, traces, and support logs.
Confirm permitted uses, model-training restrictions, breach duties, termination handling, data location, and evidence-preservation obligations.
Review pixels, tags, and session replay on appointment and portal flows.
HHS cloud guidance explains that encrypted ePHI can still create a business-associate relationship. The HHS tracking bulletin remains relevant to authenticated pages and flows that transmit identifiable health information. A June 2024 order in American Hospital Association v. Becerra vacated the bulletin’s treatment of an IP address plus a visit to an unauthenticated public health page. Do not treat every public visit as PHI on that basis; inspect the actual data flow.
For a structured purchasing checklist that parallels these diligence steps, see the AI agent buying checklist.
Integration and identity
Do not accept an EHR logo wall as integration evidence. For every action, document:
the interface and supported object;
read, write, update, cancel, and reconciliation behavior;
latency, retry, idempotency, and duplicate prevention;
sandbox parity and production monitoring;
interface fees and ownership of mapping;
the queue and accountable owner when a write fails.
Identity requirements should match the action. Public hours may need no authentication. Patient-specific appointments, balances, or records do not. A typed email, patient identifier, account ID, or phone number is a lookup key, not identity proof. Customer-specific actions require an authenticated session or a server-validated identity flow, then object-level authorization on each request. Do not collect passwords, admin tokens, or one-time codes in chat; route them to a secure login or verification screen. A guest lookup may send a secure link to the stored contact address without exposing records in chat. Test shared phone numbers, caregivers and proxies, minors, name collisions, failed authentication, account recovery, and channel changes. A failed identity check should reduce access, not invite the agent to guess.
Accessibility and language access
Test the actual agent, not only the surrounding website. Include keyboard and screen-reader use, visible focus, form labels, error recovery, captions or text alternatives, relay and TTY paths, speech impairments, and a non-agent fallback. DOJ web accessibility guidance calls out labels, keyboard access, clear instructions, and meaningful error identification. State and local entities also need to assess the Title II web and mobile rule, its WCAG 2.1 Level AA standard, and the compliance dates applicable to their entity.
Evaluate every supported language separately. Use approved translated content, varied accents and speech rates, names and addresses, code-switching, and qualified-interpreter escalation. Report accuracy and failure rates by language. Do not use a general model to improvise clinical translation.
Clinical boundary and regulation
For the administrative workflows in this guide, prohibit diagnosis, medication instructions, test-result interpretation, care-plan changes, and reassurance that urgent care is unnecessary. Route refill requests; do not generate dosing instructions. Use an immediate emergency path for urgent language.
The FDA clinical decision support guidance page, issued in January 2026, explains criteria for certain non-device CDS functions intended for healthcare professionals. Other software functions, including those intended for patients or caregivers, remain subject to applicable device policies. Human review alone does not determine regulatory status.
If the product supplies predictive decision support through certified health IT, assess whether the HTI-1 Decision Support Interventions framework applies. Its transparency model covers intended use, input features, validation, fairness, limitations, and risk-management information. Administrative scheduling software is not automatically a predictive DSI.
Ownership, model changes, and incidents
Name owners before launch: operations for the queue, clinical leadership for clinical boundaries, privacy and security for data handling, IT for interfaces and access, and the vendor for contracted service levels. Record who approves content, reviews logs, updates rules, covers after-hours escalation, and decides when service resumes after an incident.
Contract for advance notice of material model, prompt, policy, or subprocessor changes. Require version history, regression testing against your cases, acceptance thresholds, rollback rights, and revalidation after a material change.
The NIST Generative AI Profile recommends defined oversight roles, post-deployment monitoring, incident response, appeal and override, recovery, and change management. Your incident plan should classify severity, preserve evidence, set notification duties, coordinate breach analysis, correct affected records, communicate with affected people when required, document root cause, and define safe-restart criteria.
Downtime and continuity
Test outages before live use:
telephony works but the EHR does not;
the model or retrieval service is unavailable;
SMS delivery is delayed;
the human queue is closed or overloaded;
the vendor recovers after partially completing an action.
Define fail-open and fail-closed behavior per workflow, a manual fallback, status messaging, recovery-time and recovery-point expectations, queue replay, and reconciliation. “Please call later” is not a continuity plan.
An API 200 or 202 response, or a timeout, is not proof a business action completed. Read the operation state or the authoritative record. Asynchronous jobs can be pending or failed. On timeout, inspect the current state before retrying, and use idempotency or duplicate prevention so a retry does not create a second appointment or administrative task. Customer confirmation and backend success are distinct facts.
Run failure-oriented demo scenarios
A constrained reschedule with an interpreter and a same-name patient.
A caregiver acting for a patient with incomplete proxy authority.
A refill request that must route without medication advice.
Urgent language inside an otherwise administrative request.
A policy that changed yesterday and an answer cached last week.
An unsupported language followed by qualified-interpreter escalation.
Keyboard-only and screen-reader completion with an input error.
An EHR timeout after the agent says it is booking.
A transfer when the normal destination is closed.
A model or prompt version change followed by the same regression set.
Set pass thresholds before the vendor demonstration. Zero-tolerance events should include unauthorized disclosure, wrong-patient action, false confirmation of a write, and missed emergency escalation. Other metrics need a denominator and severity: correct completion, staff rework, false completion, transfer completion, identity failure, answer accuracy, accessibility success, and results by language.
Model the full cost
No healthcare-specific product in this comparison offered a public self-serve price that supported an honest monthly comparison when this guide was reviewed. Request a complete quote.
Interface licenses, mapping, test environment, monitoring
Implementation
Workflow design, content migration, language setup, training
Operations
Human review, exception handling, after-hours coverage
Assurance
Security evidence, accessibility work, testing, incident support
Compare cost per correct, reviewed outcome. Include staff time spent repairing bookings, chasing incomplete payer fields, handling exceptions, and operating the controls the vendor does not provide.
Use 14 days for readiness testing, not live deployment
A two-week exercise can test a vendor with synthetic or de-identified cases after the evidence pack is assembled. It is not enough time to complete contracting, integration, accessibility review, governance, staffing, and a safe live rollout.
Day
Readiness task
Required output
1–2
Freeze scope and ownership
One workflow, prohibited actions, accountable owners
A live pilot starts only after required contracts are executed, interfaces are validated, owners and coverage are staffed, and clinical, privacy, security, accessibility, IT, and operations reviewers approve the scope.
FAQs
Which healthcare AI agent is best?
There is no credible overall winner across unrelated jobs. Assort is relevant to specialty scheduling, Hyro to repetitive access questions, Luma to broader access orchestration, Notable to operational queues, and Infinitus to payer calls. Choose the workflow first, then compare products capable of completing it.
Do we need patient consent to use PHI for scheduling?
HHS distinguishes consent from authorization and generally permits covered entities to use or disclose PHI for treatment, payment, and healthcare operations without individual consent under the Privacy Rule. That does not resolve recording laws, state requirements, organizational policy, or contract terms. Recording a call is a separate question.
Can a public website chatbot be a low-risk starting point?
Only if the scope and data flow support that description. Patients may disclose symptoms or identifiers in free text. Inventory connected scripts, prevent patient-record access, provide a human path, and decide how unexpected health information is handled before launch.
Does signing a BAA make the product safe?
No. A BAA allocates obligations; it does not validate answer quality, identity controls, accessibility, integrations, escalation, or clinical safety. Those require separate evidence and testing.
How is this different from a medical scribe?
A scribe drafts documentation from an encounter. The products in this guide complete operational work such as scheduling, routing, intake, and payer calls. The data and systems may overlap, but the acceptance tests do not.
A defensible buying decision
Name one workflow and its prohibited actions.
Compare only products that can complete that workflow.
Require contract, integration, accessibility, language, outage, and incident evidence before live use.
Run the same failure-oriented cases and score source-system outcomes, not conversational tone.
Keep a manual path until the agent proves correct completion and recoverability in production.
The right vendor is the one that produces the required record, exposes its failures, and fits the systems and controls your team can actually operate. If those facts are still unclear after the demonstration, the correct decision is not yet.
Further reading
What to open next
4 next jobs from this page. Named destinations, not a pile of related guides.